

 2 hours ago
4
PROTECT YOUR DNA WITH QUANTUM TECHNOLOGY
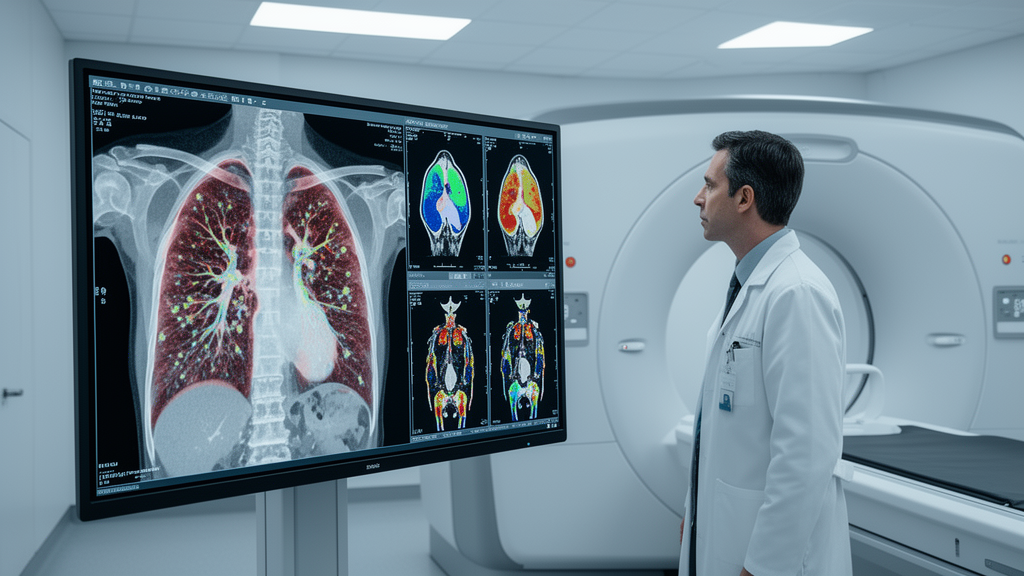
Orgo-Life the new way to the future Advertising by AdpathwayA single-center retrospective feasibility study found that intraoperative model-guided placement of temporary radiopaque anchors on the visceral pleura, followed by CT verification, was technically feasible for localizing selected small pulmonary nodules without intentional traversal of the lung parenchyma. The comparison involved 24 patients who received the intraoperative approach and 91 treated with conventional preoperative CT-guided puncture localization between January and December 2024.
Localization-category distributions were similar: 15 of 30 intraoperatively localized nodules were classified as precise, 13 as helpful and two as missed, compared with 49 of 99 conventionally localized nodules classified as precise, 42 as helpful and eight as missed. All 10 missed nodules were managed with a stepwise salvage strategy. The authors classified single-anchor intraoperative localization as precise when the anchor center was no more than 10 mm from the nearest margin of the nodule’s pleural projection; for multiple anchors, localization was precise when the projected nodule center fell within the anchor-defined target region. For conventional hookwire localization, precision was based on the three-dimensional distance between the hook tip and the nearest nodule margin, using the same 10-mm boundary.
Median intraoperative localization time was 35.7 minutes per patient, with an interquartile range of 28.8 to 47.3 minutes. One intraoperative CT imaging episode was used per patient to assess the relationship between the anchors and target nodule. When that scan showed an offset but provided sufficient spatial information, surgeons altered the direction or extent of resection without repositioning the anchors or obtaining another scan. When guidance was insufficient, the predefined fallback was thoracoscopic palpation followed, if necessary, by anatomical segmentectomy.
The workflow began with high-resolution preoperative chest CT acquired at 120 kVp, 35 mA and 0.625-mm slice thickness. An experienced thoracic surgeon processed the images in Mimics software to create a three-dimensional model containing the target nodule, lung parenchyma, pleura and adjacent structures. During surgery, the model was rotated, zoomed and reoriented to approximate the operative lung position and provide a preliminary map based on available surface landmarks. Measurements and marking were performed with the lung in a near-inflated state to account for heterogeneous deflation.
Each anchor was assembled within the sterile operative field from a 3–4-mm segment of commercially available sterile X-ray-detectable gauze containing radiopaque barium thread and sterile 3-0 silk suture. One to five anchors were positioned on the visceral pleural surface according to the model, with a round needle passed superficially through the pleural layer to draw them into position. The passage was intended to avoid the underlying lung parenchyma. The anchors were secured without knotting and held at the pleural passage site by friction. Multiple anchors could delineate a target region and the planned resection margin.
For CT verification in the hybrid operating room, the bilateral lungs were ventilated with a double-lumen endotracheal tube using a tidal volume of 10 mL/kg based on actual body weight and positive end-expiratory pressure of 8 cmH2O. This restored the operative lung to a near-inflated state but did not ensure that its geometry exactly matched the preoperative scan. Reconstructed images assessed the anchor–nodule relationship, with on-site three-dimensional reconstruction performed when required. Across 24 thoracic acquisitions, median CTDIvol was 6.87 mGy, median dose-length product was 198.5 mGy·cm, and the corresponding estimated median effective dose was 2.78 mSv. Radiation dose was estimated rather than individually measured.
No pneumothorax occurred among the 24 intraoperative patients, compared with 29 of 91 conventional-group patients, a difference reported with p<0.001. Intraparenchymal hemorrhage was observed in zero of 30 intraoperatively localized nodules and 16 of 99 conventionally localized nodules, with p=0.022. Direct nodule puncture occurred in zero of 30 and 10 of 99 nodules, respectively, while marker dislodgement occurred in zero of 30 and one of 99; neither difference was statistically significant. The sample was too small to assess rare outcomes such as systemic air embolism, although the technique did not involve intentional transthoracic needle access.
Perioperative comparisons reflected two different combined strategies. All intraoperative-group patients underwent CONSERVO electroresection, whereas the conventional group received stapler-based resection, preventing separation of the two techniques’ effects. The intraoperative strategy was associated with a shorter mean incision, 20.88 versus 30.81 mm, but longer non-localization operative time, greater blood loss, a longer chest-tube duration and greater drainage during the first three postoperative days. Median total operative time was 192 versus 75 minutes, though the latter conventional-group figure excluded hookwire placement performed separately in the radiology suite. All intraoperative-group patients had complete resection with negative margins; one conventional-group patient required completion lobectomy after incomplete resection.
The study has important limitations. It was retrospective, single-center and small, with nonrandom, indication-based treatment allocation and referral practices that could introduce selection bias. The intraoperative workflow required a hybrid operating room, preoperative model preparation, coordinated personnel and additional imaging, and its applicability to routine practice could not be established. The anchors were investigator-assembled temporary markers rather than purpose-designed devices, although prepared, placed and retrieved counts were reconciled in every case. Localization and resection methods were completely confounded, and the independent contributions of three-dimensional modeling, CT verification and CONSERVO electroresection were not determined. The findings support technical feasibility in selected patients, including those with multiple nodules or unsuitable puncture trajectories, but do not establish superiority or equivalence to established localization methods.
Subject of Research: Retrospective feasibility study of model-guided pleural anchor localization with intraoperative CT verification for selected small pulmonary nodules.
Article Title: Intraoperative model-guided anchor placement with CT verification for non-percutaneous localization of small pulmonary nodules: a retrospective feasibility study
Article References: Zhang, X., Liu, J., Zhang, S., & Li, J. (2026). Intraoperative model-guided anchor placement with CT verification for non-percutaneous localization of small pulmonary nodules: a retrospective feasibility study. Frontiers in Oncology, 16, Article 1941071. https://doi.org/10.3389/fonc.2026.1941071
Image Credits: AI Generated
DOI: 10.3389/fonc.2026.1941071
Keywords: pulmonary nodules, nodule localization, non-percutaneous localization, three-dimensional modeling, intraoperative CT, thoracoscopic surgery, pneumothorax, retrospective study, hybrid operating room, Intraoperative, model-guided, anchor














 English (US) ·
 French (CA) ·